




Opinion
“The gender pain gap hurts everyone – including the healthcare system and taxpayers”
By Cindy Moy Carr and Tami Wahl


For decades a lot of ink has been spilled both online and in print about pain treatment disparities between men and women, often by the patients themselves.
One very famous case is that of actress comedienne Gilda Radner, who in her book It’s Always Something described how she started experiencing acute exhaustion and pain in her upper legs in 1985 while filming Haunted Honeymoon in the United Kingdom.
She sought medical attention, and over the course of the next year, several doctors, the most of whom were in California, gave her differing diagnoses that ultimately turned out to be false. Several told her it was period pain and Epstein-Barr Virus which Radner herself referred to as fitting to “the Queen of Neurosis.”
For many like Radner, period pain has been blamed for what later turns out to be an unrelated illness or physical condition.
Radner continued to feel abdominal discomfort for 10 months. By the time they finally diagnosed her with Stage IV ovarian cancer in October 1986, the tumour inside her had grown to the size of a grapefruit.
Radner had a hysterectomy along with radiation and chemotherapy. Following remission and relapse, she died three years later at age 43. If only the doctors had listened and investigated all the possibilities sooner.
In November 2022, 33 years after the death of Radner, the first-ever gender pain gap report was released. The report, researched and compiled by Nurofen, based on a survey in the United Kingdom of 5,100 participants, analyses the differences in experience of pain for both men and women in the United Kingdom and found:
- 56 per cent of women surveyed, compared to 49 per cent of males, felt their pain was disregarded or neglected.
- One in four women vs one in six males reported having feelings that generally, no one took their suffering seriously.
- Of those that felt this way, 50 per cent said their GP and 27 per cent said their GP (the UK equivalent of a PCP) ignored or dismissed their pain, with partners/spouses (26 per cent) and friends (21 per cent) reacting in similar ways.
- Nearly two-thirds (63 per cent) of women believe that doctors and nurses discriminate against women and treat men’s pain more seriously.
The reasons it took so long for such a study are present in the results. The report states that the gender gap found in this study is probably a product of a “male as default” philosophy and historic practice that pervades research, clinical trials, healthcare policy and services.
It seems Radner wasn’t the only one who thought herself neurotic. The report also states that only 28 per cent of women who experience severe daily pain would seek consultation with their GP.
That trend continues with treatments for pain where 74 per cent of women would choose self-care over seeing an GP due to feeling ignored or dismissed compared to just 60 per cent of men. And almost a quarter (24 per cent) of the women surveyed also reported that pain had led to them feeling depressed, compared to 18 per cent of men.

These results, while shocking, are an everyday experience for most women we know.
The first study definitively proving the existence of menstrual pain was released by Harvard and Apple in March 2021. Women obviously knew menstrual pain existed, the pain simply wasn’t considered important enough to merit research funding.
In 1998 sildenafil citrate, later marketed as Viagra, was tested as heart medication and found to offer total relief for serious period pain over four hours. The review panel refused further research funding because cramps were not a public health priority.
In 2007 sildenafil citrate was found to help hamsters recover from jet lag. In 2013 sildenafil citrate was again shown to relieve menstrual pain but the study ran out of funding. Hamsters get priority over women.
More recently one of this article’s authors sought counselling for hypochondria after numerous doctors told her the mysterious ailments she was suffering, including debilitating migraines, dry eyes and vertigo, were psychosomatic.
It was a nurse who told her it was perimenopause. Simple hormone therapy solved years of symptoms.
Gender pain disparity is a safety issue
In 2020, the First Do No Harm report was published by the Independent Medicines and Medical Devices Safety Review, chaired by Baroness Julia Cumberlege.
The Review team spent two years speaking to more than 700 women and their families who experienced complications linked to three treatments–1) sodium valproate, an epilepsy drug that increases the risk of birth defects; 2) Primodos, a hormonal pregnancy test withdrawn from the market in 1978, allegedly associated with birth defects and miscarriages; and 3) pelvic mesh implants, used to treat prolapse and urinary incontinence, the complications of which can cause debilitating pain “like shards of glass inside the body”.
The 277-page report is an explicit and gut-wrenching read, laying out in minute detail the multitude and shocking ways in which patients – most of whom are women – were treated dismissively by the healthcare system with the resulting outcomes being just as severe, including job loss, breakdown of family life, children or husbands becoming carers for mothers or wives, and for women with children suffering from foetal valproate spectrum disorder, being accused of abuse by poorly educated clinicians.
On page 17 of the report, under the subtitle ‘No-one is listening’ – The patient voice dismissed, the Review team writes: “They spoke of being ‘gaslighted’ and of not being believed, particularly in relation to pelvic mesh and the suffering of pain.
“Women, in reporting to us their extensive mesh complications, have spoken of excruciating chronic pain feeling like razors inside their body, damage to organs, the loss of mobility and sex life and depression and suicidal thoughts.”
The Review team goes on: “Some clinicians’ reactions ranged from ‘it’s all in your head’ to ‘these are women’s issues’ or ‘it’s that time of life’ wherein anything and everything women suffer is perceived as a natural precursor to, part of, or a post-symptomatic phase of, the menopause.”
The Review then explains some of the consequences of this treatment, including the increased costs to the UK taxpayer.
“We know that women who accept a normalisation of their pain tend to seek the help they need far later than they should,” they write.
“This precludes the possibility of early, less invasive treatment with potentially better outcomes. It also takes its toll, physically, mentally and emotionally on the patient and their family and imposes ultimately a far greater cost on the NHS and the healthcare system to treat and attempt to put right.”
What steps can we take to narrow the gap?
Nurofen’s study is a good start. They’ve also launched a website called named See My Pain where the stories of real women are posted.
Their parent company Reckitt Benckiser has also committed to several long-term initiatives that go beyond marketing to finally close the gender pain gap.
For instance, the business will invest in creating new tools to help both men and women describe and articulate their suffering while speaking with medical specialists.

Reckitt has also pledged to include gender balance when planning and analysing its clinical studies, provide training in identifying gender bias and will frequently review the Gender Pain Gap Index Report to monitor progress. (Note: The authors are not affiliated with Reckitt.)
These are all good first steps from a brandholder in the medical ecosystem.
Healthcare professionals could receive training in active listening techniques. Medical school curriculums and continuing education sessions could explore and raise awareness of the gap, which may initiate an openness and curiosity for students and physicians to look beyond defined conditions.
Patients should learn to be their own advocates. Today we have technologies, digital platforms, social media and online communities to better inform and empower an individual.
Perhaps if Gilda’s medical team was more curious or she had a broader support network with similar symptoms she wouldn’t have dismissed herself as “neurotic” and she’d still be here making us all laugh with her wonderful characters.
A longer-term and more involved measure is a comprehensive and macro-review of the healthcare model.
The system has become such a behemoth that medical discoveries and any sense of individualised treatments are ultimately limited if non-existent.
The existing model was built decades prior to the array of digital data and technologies that are available today. Is a complete overhaul needed or can the existing system be reconfigured to utilise and meet contemporary times?
A serious review would reveal best next steps to close the gender pain gap among other improvements.
The Nurofen report concludes on a practical note: “Closing the gap on pain will not only provide immediate solutions for women experiencing pain, but we hope will have a ripple-effect in terms of social and economic gains.”
More importantly, closing the gender pain gap will save lives and will absolutely improve the quality of life for women navigating pain.
Cindy Moy Carr is the founder and CEO of Vorsdatter Limited which developed mySysters, an app for perimenopause and menopause. She’s an attorney and journalist who authored the American Bar Association’s Guide to Health Care Law.
Tami Wahl serves as legislative and regulatory counsel for innovators across multiple industry sectors.





A new clinical study has found that an at-home device for tracking reproductive hormones can identify ovulation with an accuracy that closely matches hospital-grade ultrasound scanning, in what researchers describe as a significant step for women’s health technology.
The findings, published this week in Reproductive BioMedicine Online, come from an 18-month trial led by Dr Thomas P. Bouchard that followed 121 ovulatory cycles and included 890 transvaginal ultrasound scans.
The study compared results from the Mira at-home hormone monitor, which tracks four hormones through urine samples, against the two methods long considered the clinical gold standard: ultrasound-confirmed ovulation and blood serum testing.
Researchers found that the day of ovulation, as confirmed by repeated ultrasound scans, fell within a day of the peak in luteinising hormone (LH) detected by the device in 96 per cent of cycles studied.
A new benchmark after 25 years
The study’s authors say it represents the first time a quantitative, multi-hormone at-home monitor has been validated against blinded ultrasound scanning under STARD guidelines, the internationally recognised standard for reporting diagnostic accuracy research.
Existing consumer fertility trackers, they note, have largely relied on simpler yes/no hormone readings or date-based algorithms that have gone unchanged for a quarter of a century.
The device tracks four hormones: LH, the oestrogen metabolite E13G, the progesterone metabolite PDG, and follicle-stimulating hormone (FSH).
What the data showed
Alongside the headline ultrasound comparison, researchers reported several other findings:
- Blood test correlation: readings from first-morning urine samples closely tracked blood serum levels drawn within 90 minutes, with the strongest correlation for LH, followed by progesterone and oestrogen metabolites, and a weaker but still notable link for FSH.
- Hidden variability in “regular” cycles: even among participants with typically regular periods, 11 per cent of cycles were found to be anovulatory, meaning no egg was released. In a further 12.4 per cent of cycles, ovulation occurred while LH was still climbing rather than after it peaked – a pattern researchers say calendar-based apps and single-day tests would likely miss.
- Earlier warning of fertility window: rising oestrogen signals were detectable roughly five to six days before ovulation, reflecting the natural development of ovarian follicles and offering an earlier indication of the fertile window than LH tracking alone.
‘Precise biological data without the clinic visits’
Dr Bouchard, the study’s lead author, said the research set a new bar for evaluating consumer fertility devices.
“For over two decades, at-home fertility tracking was based on qualitative indicators without providing quantitative hormone values,” he said, adding that testing the device against nearly 900 ultrasound scans under a blinded protocol gave the field a rigorous new benchmark.
Sylvia Kang, founder and chief executive of Mira, said the results pointed to a broader shift in how reproductive health could be monitored.
“Women deserve precise biological data about their reproductive health without needing constant clinic visits and serial blood draws,” she said, describing the findings as evidence that at-home testing could deliver “clinic-grade hormonal visibility.”

Sahar Abid is a Science Associate at Ema EQ, where she works on cultural sensitivity and bias in AI.
A woman asks an AI health assistant about postpartum depression.
She mentions that her in-laws are telling her to “push through” and skip medical help, even as her symptoms get harder to manage. She never says where she is from or names her background.
The assistant describes the condition and gives her a hotline number. It sounds correct, but it misses what she needs.
That gap is more common than the industry admits, and it points to a blind spot in how we test health AI for bias.
Most bias testing looks at what people explicitly say.
The typical way to check an AI for bias is to label a prompt with someone’s demographic details and see if the answer changes. That catches some problems but misses a bigger one.
Most people do not lead with their identity. They lead with their situation. The woman above told the assistant everything it needed to help her, just not in the form of a label.
Her real question was not only “what is postpartum depression?” It was “how do I get care when the people around me don’t want me to?
When family members hold sway over health decisions, and in many communities they do, advice that asks someone to overrule their family is not something they can act on.
The AI didn’t say anything factually wrong. It answered a different question than the one she was living.
We call this culturally implicit bias, meaning the AI misses the cultural context a situation implies rather than the context a person spells out.
When systems are trained to notice only the explicit cues, they fall back on a default answer built for the majority. For everyone else, the response can feel generic, off-target, or discouraging enough that they stop looking for help.
In health, that is not small. The people most likely to be missed are often the ones the system already underserves.
What we set out to test.
At Ema, we wanted to know how well AI picks up on cultural context that is implied but never stated. So we built our own way to test for it, across a range of communities and real situations like postpartum depression and fertility, using questions that carried cultural meaning without announcing it.
The patterns were consistent. Models often missed the meaning underneath the question. They dropped the specific details a person did share and smoothed them into something generic.
And even when they pointed toward real care, they tended to offer one option instead of choices that might actually fit a person’s life. Any one of those can be the difference between someone following the advice and walking away from care.
Why this matters for anyone building health AI.
Getting this right is the right thing to do, and it also works better.
When an answer reflects a person’s real context, people trust and act on the recommendations more, so they get the help and support they need.
Testing for it is harder than the shortcut most teams use. Swapping a name or a demographic label in and out is easy. Checking whether a model actually understands the human context around a question takes more care.
The shortcut teaches models to perform cultural competence instead of practicing it. No matter how much or how little someone chooses to share, they deserve an answer that is warm, complete, and usable.
A better question.
The bar for equitable health AI should be “does it serve someone who never told you who they are?” It is the harder test, but it determines whether real people get help.
The work of getting there is far from finished, and it is exactly what we are building toward at Ema.
Sources: Naidoo, V., & Chadha, K. K. (2025), Culturally responsive AI chatbots: from framework to field evidence, Computers in Human Behavior: Artificial Humans. Souligne, N., & Subbian, V. (2026), FairLogue: A toolkit for intersectional fairness analysis in clinical machine learning models.


A perimenopause app that maps existing smartwatch data to the menopausal transition has launched across 39 markets in the UK and Europe.
anna app uses information already recorded by wearables, including sleep, heart rate and body temperature, and returns one suggested lifestyle action each morning alongside the research behind it.
The company says each rule in its library links a defined pattern in a woman’s own data to a specific action. The recommendations were developed with an advising clinician and draw on more than 300 published studies.
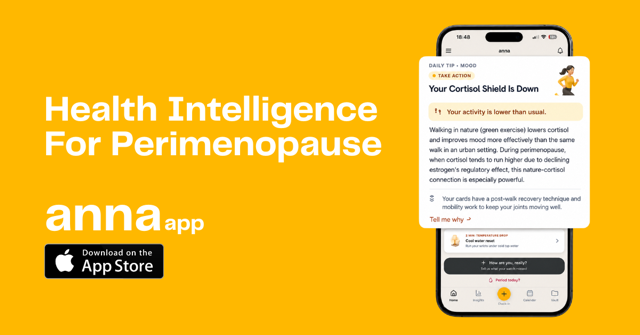
The company says recommendations are not generated automatically and each can be traced to research reviewed by a doctor.
The app was built by two women in Riga, has been funded without outside investment and was tested with women in the UK over three months before launch.
Perimenopause is the period of hormonal change before periods stop and usually begins after 40.
The company says one of the challenges is the unpredictability of the transition, with sleep, energy, mood and concentration potentially changing from week to week.
Because the experience varies between women, the developers say it can be difficult to find care tailored to individual needs. After 45, there is also no reliable blood test to confirm perimenopause.
The transition can coincide with a busy period in women’s working lives.
CIPD research published in 2023 found that 27 per cent of working women aged 40 to 60 with menopause symptoms said they had affected their career progression, equivalent to around 1.2m women in the UK.
Some 79 per cent said they felt less able to concentrate.
The long-running Study of Women’s Health Across the Nation, which has followed thousands of women through the menopausal transition, found that cognitive difficulties reported during perimenopause appear to be time-limited, with improvement returning in early postmenopause.
The developers say anna differs from standard wearable data by interpreting measurements specifically in the context of perimenopause.
A smartwatch may show changes in sleep, heart rate or temperature, but anna is designed to look at combinations of those signals and link them to lifestyle guidance for that day.
The app is also designed to work without daily symptom logging.
Users can complete an optional daily check-in if they want to add more context, but the app can operate without a symptom diary or daily manual entries.
It uses information from a compatible device the user already owns, such as a watch, ring or band.
Elina Pika-Lepere, co-founder and chief executive of anna app, said: “Perimenopause arrives exactly when a woman has the least spare capacity. She is often at the peak of her career, raising children, caring for ageing parents. What she has lost is not information, it is predictability.
“We built anna to offer a helping hand and evidence-based guidance through a stage that is difficult but temporary.”
The company gave the example of a morning when a user’s watch shows she has slept well below her own 28-day average.
Rather than simply telling her she is tired, anna may suggest choosing one priority and working on it in 25-minute blocks with a short break between them.
The app also displays the sleep and concentration research used for the recommendation.
anna was founded by Pika-Lepere, who spent 15 years building products in advertising, retail and e-commerce, and product lead Zanda Freimane, whose background is in product management in fintech and e-commerce.
The wider team includes a mathematician and university researcher advising on data architecture, a senior developer and a user experience adviser from a Baltic unicorn company.
anna app is not a medical device and does not provide medical advice.
Its guidance is limited to lifestyle support, and the company describes the app as a tool to complement a doctor rather than replace professional medical care.
anna app is available on iOS across 39 markets in the UK and Europe and is listed on the App Store as anna: Perimenopause & Sleep.
The app is in English and works with Apple Watch, Garmin, Fitbit, Oura and Whoop through Apple Health.
The company says user data is hosted in the EU and is never sold.
The service costs £13.99 a month or £99.99 a year in the UK and €14.99 a month or €99.99 a year in the euro area after a seven-day free trial.










 Ageing7 days ago
Menopause may not explain rising heart condition in women – study

 Entrepreneur2 weeks ago
Last chance to save on Women’s Health Week and Women’s Sport Summit: Early Bird pricing ends 11 September

 Fertility2 weeks ago
Paracetamol use may impact future fertility, studies suggest

 Insight7 days ago
Women with birth trauma face 2.5x higher healthcare costs – study

 Menopause2 weeks ago
Cancer drug could tackle osteoporosis menopause weight gain

 News6 days ago
Medical cannabis may improve endometriosis symptoms – study
 Cancer7 days ago
Study could explain why obesity is a breast cancer risk factor

 Diagnosis2 weeks ago
FDA approves AstraZeneca breast cancer drug
1 Comment