




Pregnancy
Understanding the contraception crisis
How the one-size-fits-all approach fails women and why it has to change

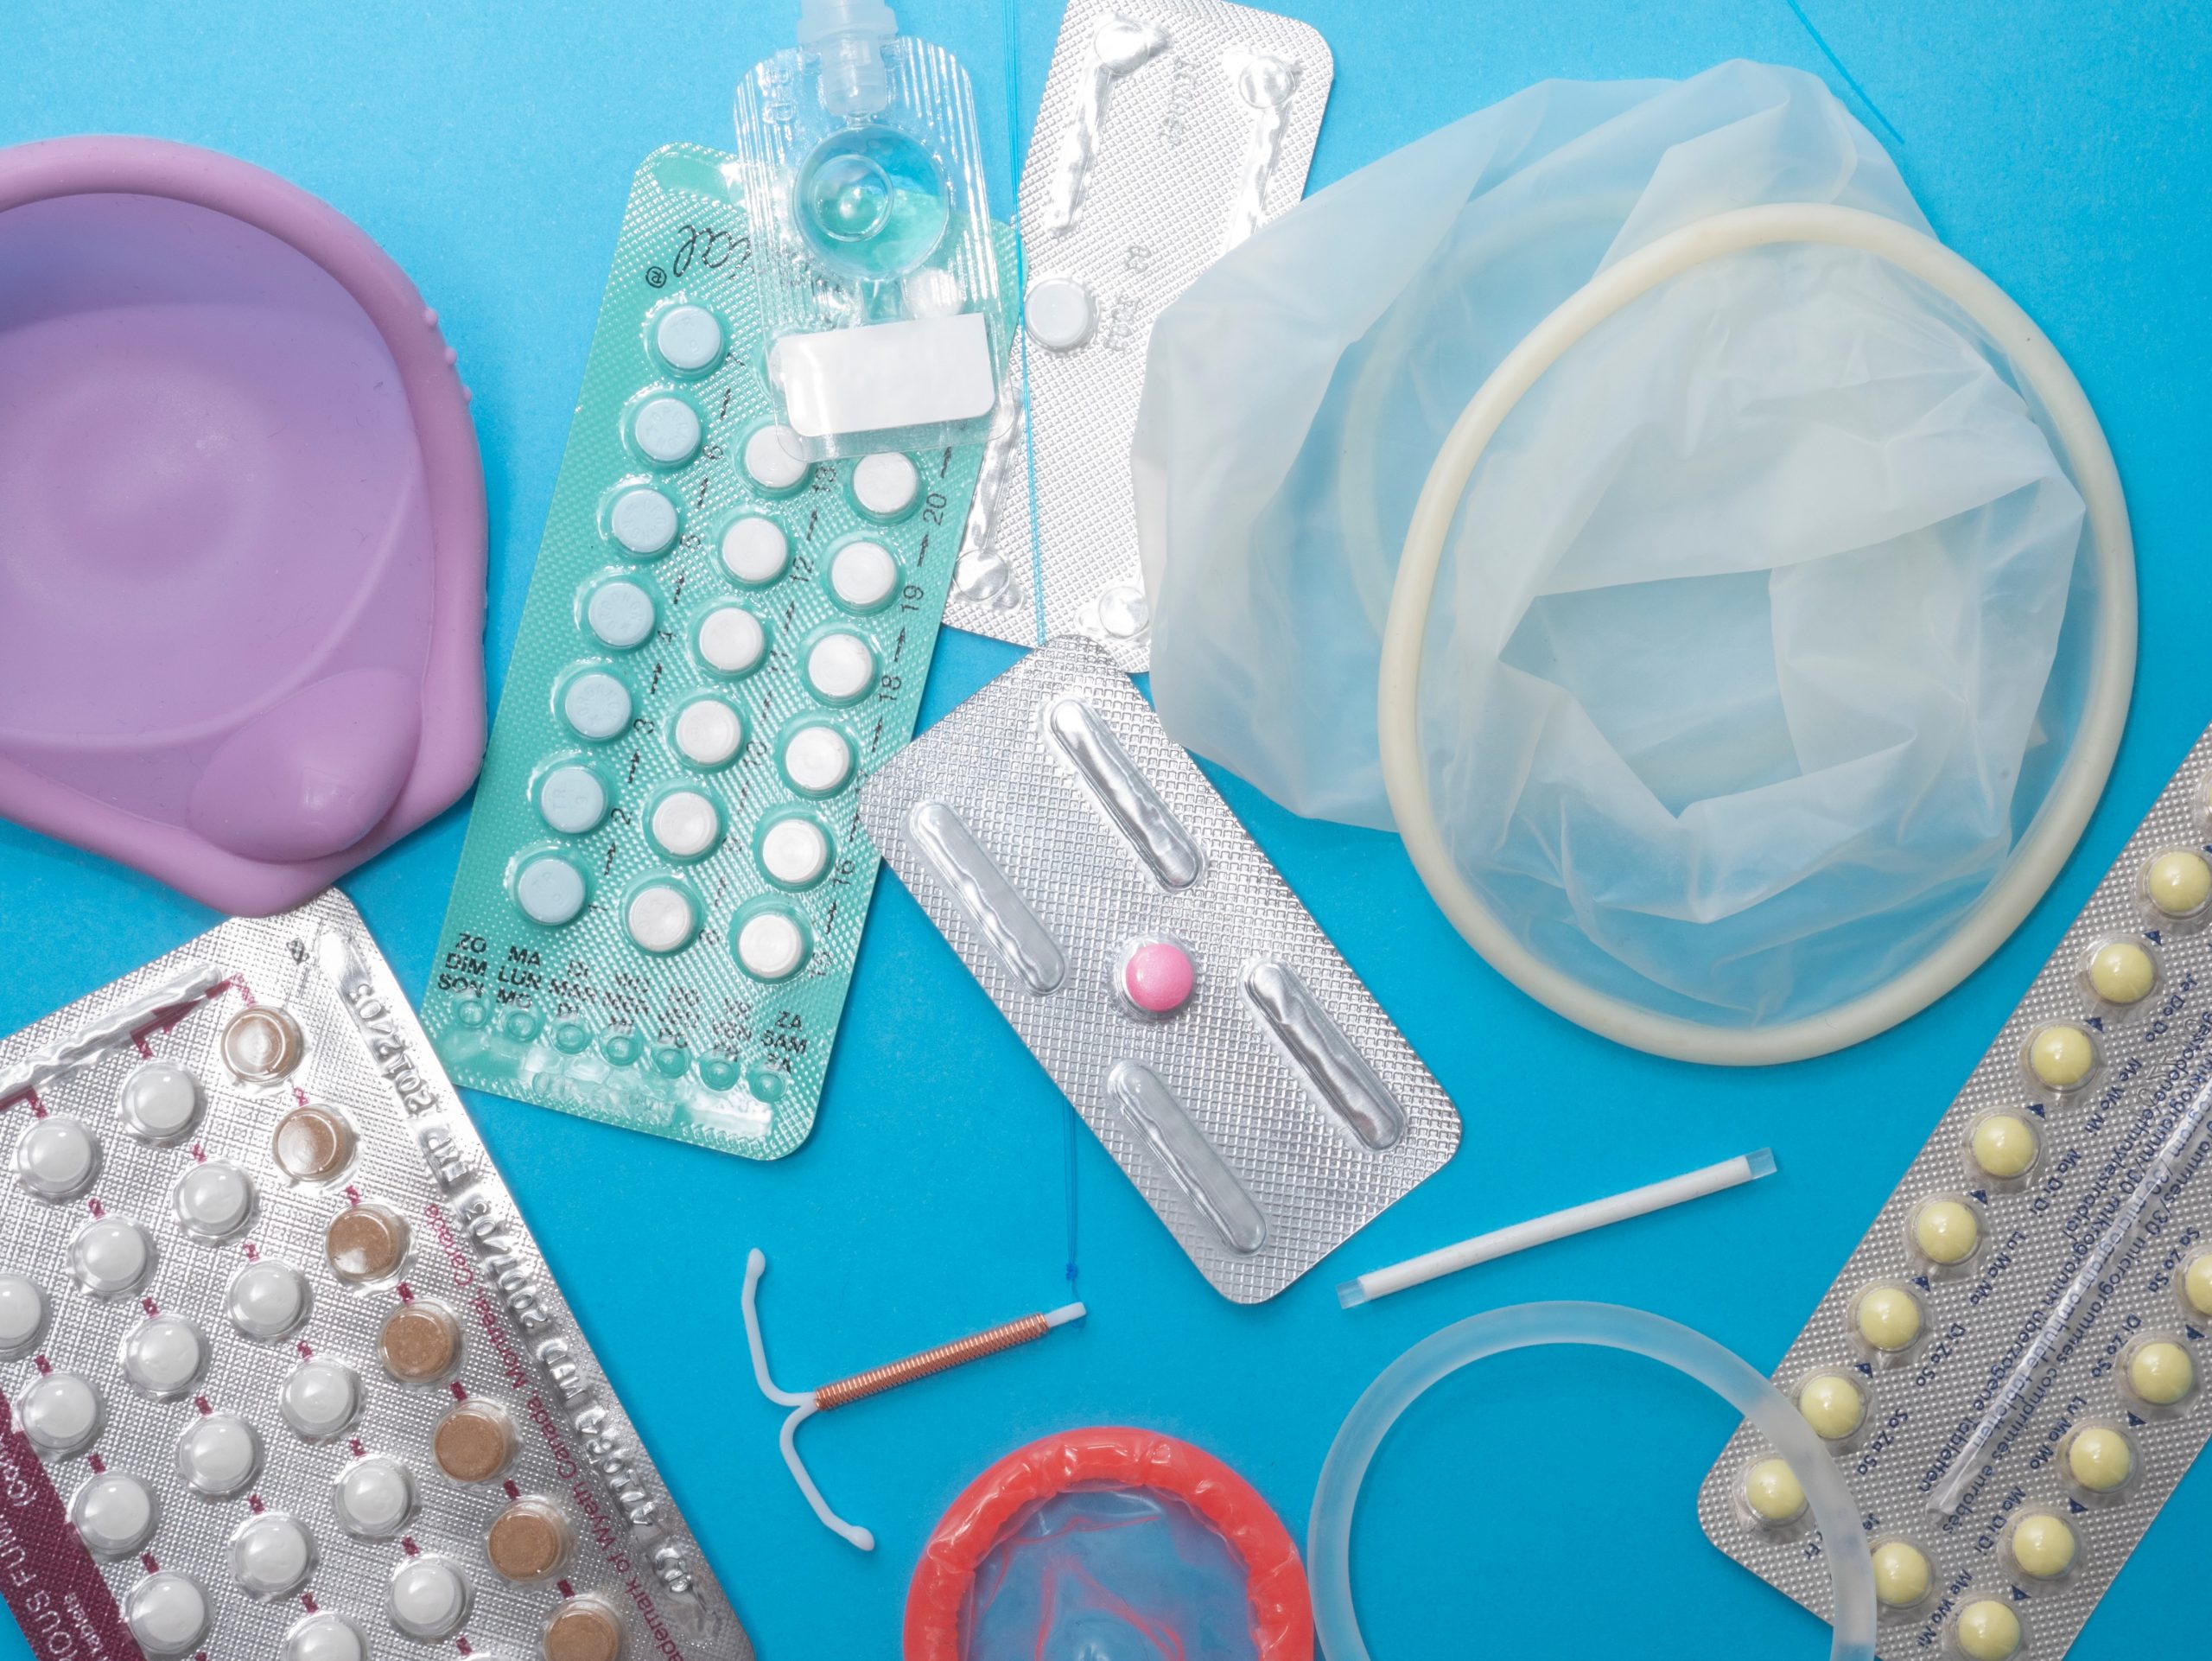
Finding the right contraception method shouldn’t be trial and error, says Elena Rueda Carrasco. She tells FemTech World why understanding contraception is more important than ever.
“Despite encouraging research, a male birth control pill remains elusive,” reads a recent headline in The New York Times.
Although, according to the article, scientists have been researching ways to create a male birth control pill since the 1970s, negative side effects, such as weight gain, acne, irritability and mood swings, have been responsible for not licensing any products for use.
“A woman can struggle with the same symptoms in silence – something rather normalised in our society,” says Elena Rueda Carrasco, medical scientist and co-founder and CEO of Dama Health, a company that offers personalised contraception recommendation. “Many women are being told from a very young age that the pain they are experiencing is normal,” she adds.
Indeed birth control side effects, such as weight gain, mood changes and headaches, affect eight in ten women, but are yet deemed too dangerous for developing a pill for men.
“The side effects and the impact of different contraception methods on women have been very normalised when you compare it to other areas of medicine,” Rueda explains. “In a lot of cases, women end up with conditions like endometriosis and PCOS – polycystic ovary syndrome – because their symptoms are often ignored and early diagnosis is not achieved.”

Elena Rueda Carrasco, co-founder and CEO of Dama Health
Figures suggest that medical consultations are too short to offer the right guidance and on average, women try 3.5 different contraceptive methods before finding the one that works for them.
“In the UK, we have such a fragmented [health] system,” the co-founder says. “As a woman, you can get your contraception through your GP, you can go to a sexual health clinic, you can speak to a nurse or a pharmacist. And from our own research, we found out that for many women, this is very confusing.
“Most of the time women will probably call or visit their GP and the GP is actually not a specialist,” Rueda points out. “The GPs are doing a bit of everything, with just a couple of contraception methods they’re comfortable prescribing. Therefore, communication is really hard when you have this fragmentation happening and you don’t really know where to go and who to speak to”.
Dama Health aims to personalise and tailor the way women are being prescribed contraception, screening for and identifying the side effects that women might experience individually. An algorithm would then match them to the recommended contraceptive options that are most suitable for them.
“As a team, we are all scientists and doctors by background, and we were all experiencing this problem of trial and error in the way that women were being prescribed hormonal medication and in this specific case, contraception,” the CEO says.
“I think it all came from personal experience and we all felt that it was an issue. Our chief medical officer, Dr Aaron Lazorwitz, is an OBGYN doctor and he experienced it in clinic, whereas myself and Paulina Cecula [her co-founder] experienced it as women. Paulina is also a medic and she was seeing that actually, doctors were having difficulties and the whole thing ended up being like ‘try this and come back if there’s a problem’.
“We thought that there’s a huge inefficiency [within the system] in this day and age. Women shouldn’t be having to trial and error to find if something is good for them,” Rueda adds. “So that drove us to start doing screening tests, making everything a lot more personal and helping the medical community to make the best decisions when it comes to contraception methods.”
She says that at the heart of this, education and communication are extremely important. “Women and young adults need to be educated around the topic of contraception better,” the CEO says.
“Women especially feel unable to verbalise how they feel, they can’t actually communicate it. So part of our solutions through the screening process, is to ask the right questions that help women understand their bodies and have a better conversation with their doctor.
“For that reason, I think personalised medicine is the future because actually, this one-size-fits-all approach isn’t working. When it comes to medication, you really do need to get that personalisation because the inside of us is so different and so unique.
“With technology becoming cheaper, we have the tools and the ability to make it more personalised and that essentially means taking into account medical history, preferences, maybe some biomarker information and just putting them together to be able to tailor the right treatment option.”
Experts like Rueda believe that very often huge amounts of data are being lost because of a lack of a data tracking system and that subsequently, makes the entire research process harder. “A doctor doesn’t tell you ‘Hey, try this contraception and tell me how you feel’ and actually write a report on it,” she explains. “That information is, therefore, not being captured. That’s dangerous because so much information is not being taken into account.”
But how could data tracking help the medical world? “A doctor is always going to use quantitative and qualitative data to make decisions, so symptom-tracking is one of the most powerful things that we can do as patients,” Rueda adds. “Data has so much power because it helps you essentially prove your point in an argument and is the fastest way to get information and to accelerate research.”
Walking into the clinic, as a woman, and feeling empowered is something that the CEO would like to see in the future and she also hopes that her company will support all women equally.
“The most important thing [for Dama Health] is to be able to be as accessible as possible and help women from different backgrounds. That impact is really important for us and also just working with the medical community and trying to implement our screening tests that could be easily accessed by anyone.”
The team will also be recruiting for beta testers and clinical in Q4 of 2022. If you are UK-based, you can sign-up here to be part of future clinical trials and research programmes.
For more info, visit damahealth.com.






Women entering pregnancy with multiple long-term health conditions face higher risks of miscarriage and other complications, a UK study found.
Those with two or more pre-existing physical or mental health conditions had a 20 per cent higher risk of miscarriage than women with no long-term conditions.
They also had more than twice the risk of venous thromboembolism and around four times the risk of antenatal anxiety and depression.

The UK-wide research team analysed 2,225,701 pregnancies and birth events recorded between 2000 and 2022 across five datasets covering England, Scotland, Wales and Northern Ireland.
Women with multiple long-term conditions had a 69 per cent higher risk of nausea and vomiting during pregnancy and a 42 per cent higher risk of pre-eclampsia.
The women also had a 32 per cent higher risk of placental abruption and a 26 per cent higher risk of gestational diabetes.
Risks rose as the number of existing conditions increased.
Among women with three or more long-term conditions, the risk of venous thromboembolism was more than three-and-a-half times that of women with no long-term conditions.
Researchers said the findings had implications for maternity services, where care pathways are largely centred on individual conditions and may not adequately meet the needs of women with multiple long-term conditions.
Dr Kelly-Ann Eastwood, joint senior author and honorary lecturer at Queen’s University Belfast and consultant obstetrician at St Michael’s Hospital, Bristol NHS Foundation Trust, said the results “help define” the urgent clinical challenges facing women entering pregnancy with multiple long-term conditions and the clinicians caring for them across the UK.
“These findings highlight the pressing need to restructure existing maternity services to improve antenatal outcomes,” she added.
The authors cautioned that the study was observational and relied on routinely collected health records, meaning some conditions and outcomes may have been under-recorded, while residual confounding could not be excluded.
The researchers plan to examine birth and child outcomes and identify which combinations of long-term conditions carry the greatest risk.



Ultrasound Direct has extended its Trice Imaging partnership for three years, adding a reporting tool across its 70-clinic UK network.
The private ultrasound provider will continue using the Tricefy platform for secure image storage and patient engagement, alongside TriceIQ for efficiency and productivity analytics.
It will also introduce Trice Workspace Reporting across its network. The companies say the tool will help standardise ultrasound reporting templates and workflows and reduce variation between clinics.
Ultrasound Direct carries out an estimated 120,000 patient scans each year across services including pregnancy, fertility, women’s health, men’s health and other diagnostic pathways.
Its network uses a large pool of sonographers working across different ultrasound systems and serves referral routes including self-referring patients, GPs and commercial partners.
Mike Steward, founding director at Ultrasound Direct, said: “Having worked with Trice Imaging since 2018, we first partnered to replace manual methods of providing scan images to expectant parents with Trice’s secure electronic image-sharing platform. Today, every study performed across the Ultrasound Direct Network is recorded and stored on Tricefy, while our clinical services have expanded considerably beyond pregnancy into fertility, women’s health, men’s health and other diagnostic pathways.”
He added: “To continue futureproofing our image management strategy across a network of 70 clinics, a large team of sonographers, varying ultrasound systems and a growing number of referral partners with different needs, we decided to extend with Trice Imaging. This includes the introduction of the new Trice Workspace Reporting module to help us scale and standardise our ultrasound reporting templates and workflow, reducing variability between clinics.”
The partnership began in 2018, initially focusing on replacing manual methods of sharing pregnancy scan images with expectant parents.
Johanna Wollert Melin, founder and chief executive of Trice Imaging Europe, said: “Ultrasound Direct has been a valued partner in the UK for 8 years.”
She added: “At the heart of the relationship is a willingness to explore new ideas, test new tools and the spirit to solve real challenges across a large and complex clinical network.”
Mark A. Samii, chief revenue officer at Trice Imaging, said: “We are delighted to retain and extend our relationship with Ultrasound Direct.”
He added: “The addition of Trice Workspace Reporting addresses a challenge we hear from multi-site providers globally – keeping reporting quality consistent across many users, systems, referral or payer relationships.”
Steward said Ultrasound Direct continues to see growing demand for private diagnostics alongside NHS care from self-referring patients and an increasingly diverse range of professional and commercial referral partners.
He added: “As that development continues, scalable digital infrastructure becomes increasingly important. Our focus is on ensuring that a growing national network can support consistent clinical workflows, different referral pathways and the technology requirements of the future, while continuing to provide patients with accessible diagnostic services.”

Paracetamol use in pregnancy was not linked to autism or ADHD, while separate research found reproductive differences in girls exposed before birth.
One study analysed health records from more than 120,000 children and found no increased risk of autism following prenatal paracetamol exposure.
A separate analysis of nearly 100,000 children also found no increased risk of ADHD among those born to mothers who used the painkiller during pregnancy.
Researchers from the Hong Kong Hospital Authority examined electronic health records covering pregnancies between January 2001 and December 2023.
The autism analysis included 124,333 children, who were nine years old on average and split almost evenly between males and females. There were 3,445 autism diagnoses, representing 2.8 per cent of the group.
The ADHD analysis involved 97,285 children, who were seven years old on average and also split evenly between males and females. There were 5,168 ADHD diagnoses, representing 5.3 per cent.
Women prescribed paracetamol during pregnancy were more likely to be older and have pre-existing conditions including psychiatric disorders, as well as reasons for taking the drug such as infection, fever or chronic pain.
No association was found between prenatal paracetamol exposure and either autism or ADHD.
The findings did not differ according to the trimester in which paracetamol was taken or whether use was intermittent or daily. Advanced maternal age, defined as pregnancy in women over 35, did not alter the findings.
The researchers wrote: “Paracetamol remains a safe and essential analgesic [pain reliever] and antipyretic [fever reducer] during pregnancy, whereas alternatives, such as NSAIDs and opioids carry well-documented risks.
“Unwarranted reluctance to use paracetamol could lead to undertreatment of pain and fever, or the use of more harmful alternatives, both posing risks to the pregnancy and developing fetus.”
The authors said women should assess paracetamol use with guidance from their doctor.
A separate study involving 685 pregnant women without pre-existing conditions and 302 infant daughters found associations between prenatal paracetamol exposure and differences in reproductive organs and hormone levels.
Researchers from Copenhagen University Hospital enrolled the women during their first trimester and assessed them during the first trimester, third trimester and again when their babies were three months old.
At around three months, infants experience a temporary rise in reproductive hormones sometimes called mini-puberty.
Pregnant participants completed questionnaires every two weeks about their use of pain medicines including paracetamol. Infant girls underwent ultrasound scans of their reproductive organs and blood tests to measure hormone levels.
Researchers also examined a separate group of 1,210 girls followed from infancy to adolescence whose mothers reported paracetamol use during the third trimester.
Three-month-old girls exposed to paracetamol before birth had an average 40 per cent smaller ovarian volume, 13 per cent smaller uterine volume and 23 per cent fewer ovarian follicles.
Girls exposed during the first trimester also had lower levels of Anti-Müllerian hormone, a marker of ovarian function.
Among the older girls, those exposed before birth were more likely to have smaller uteruses at puberty and smaller ovaries during their teenage years.
Dr Margit Bistrup Fischer, lead study author and postdoctoral researcher in the Department of Growth and Reproduction at Rigshospitalet hospital in Denmark, said: “Animal studies have demonstrated that impaired formation of ovarian follicles can lead to reduced fertility and earlier reproductive aging.
“Whether the differences observed in our study have implications for fertility and age at menopause in humans remains unknown and will require long-term follow-up of the girls in our cohort.”
She cautioned that women who had used paracetamol during pregnancy “should not be alarmed by our findings”, as the study found associations rather than direct causation and outcomes for individual women and children are unclear.
“Importantly, our study does not evaluate whether [acetaminophen] causes reproductive problems, nor does it provide evidence that prenatal exposure affects future fertility or age at menopause,” she said.
“Although we observed similar associations in an independent cohort, long-term follow-up is needed to determine whether these early-life differences have any clinical significance later in life.”










 Menopause6 days ago
Menopause may not explain rising heart condition in women – study

 Fertility1 week ago
Paracetamol use may impact future fertility, studies suggest

 Entrepreneur2 weeks ago
Last chance to save on Women’s Health Week and Women’s Sport Summit: Early Bird pricing ends 11 September

 Insight6 days ago
Women with birth trauma face 2.5x higher healthcare costs – study

 Menopause2 weeks ago
Cancer drug could tackle osteoporosis menopause weight gain

 News5 days ago
Medical cannabis may improve endometriosis symptoms – study

 Cancer6 days ago
Study could explain why obesity is a breast cancer risk factor

 Diagnosis2 weeks ago
FDA approves AstraZeneca breast cancer drug
Pingback: Pill problems: Why are women still struggling to access the right contraception, and how can healthtech help? - FemTech World